

Caring for a bedridden person at home comes down to a few routines: a bed and mattress that take pressure off the skin, repositioning on a schedule a nurse or doctor sets, daily skin checks, safe feeding, and enough trained hands to move the person without anyone getting hurt. In New York, Medicare and Medicaid can each pay for part of the equipment, and Medicaid may pay for personal care hours. Medicare does not pay for ongoing custodial care.
How do you set up a room for someone who is bedridden?
Start with the bed. A hospital bed lets the head and legs be raised and lowered and accepts add-ons such as a trapeze bar. Add a pressure-reducing mattress or overlay. The National Institute on Aging (NIA) suggests a pad filled with foam, gel, air or water on top of the mattress, fitted snugly, and says a nurse, aide or therapist can show you how to use it.
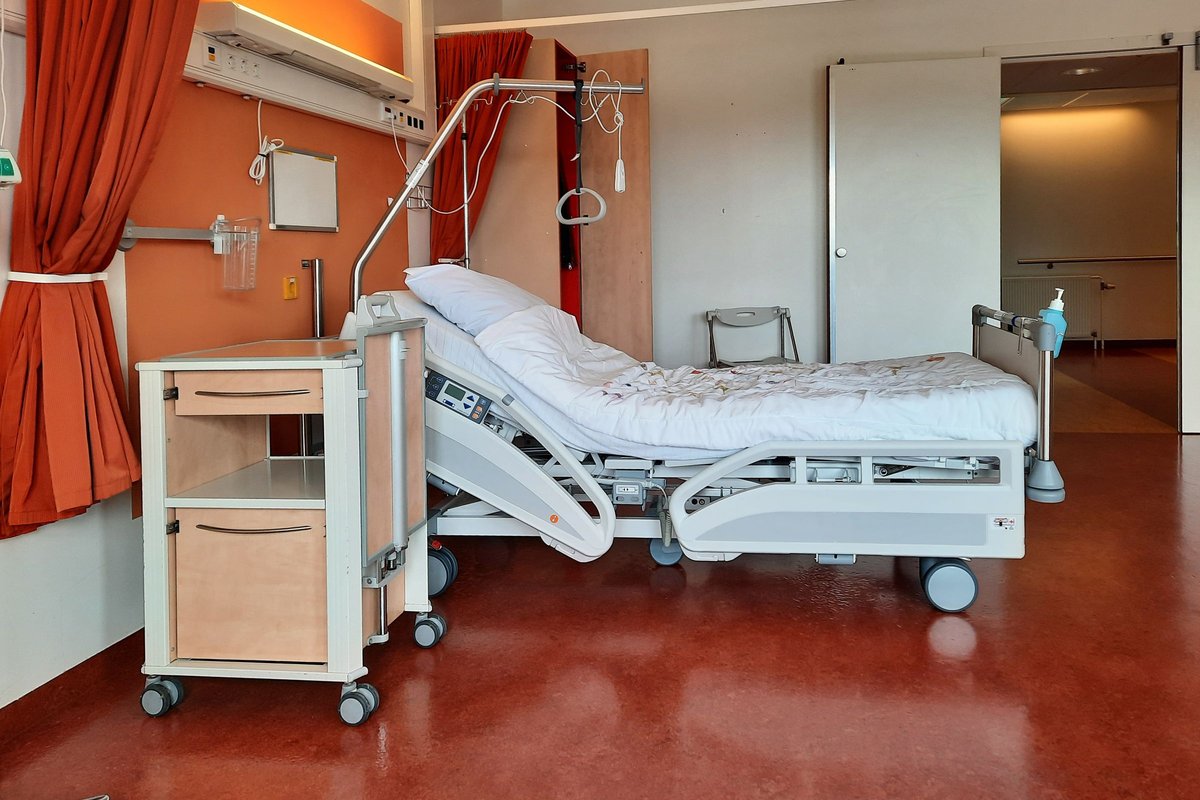
- A written turning schedule at the bedside. The AHRQ pressure ulcer toolkit lists this as a basic practice.
- Pillows to lift pressure points and heels off the mattress. AHRQ’s sample plan for bed-bound patients includes this. Ask the nurse where to place them.
- Clean, dry, wrinkle-free linens, which AHRQ’s sample plans list for friction and moisture problems.
- Water within reach. AHRQ suggests offering a sip each time you enter the room, since dehydration predisposes people to pressure ulcers.
Will Medicare or New York Medicaid pay for a hospital bed and special mattress?
Often yes, if a doctor orders them and the person meets the rules. Medicare.gov says Part B may cover a hospital bed when it is medically necessary and prescribed for use at home. After the Part B deductible you pay 20% of the Medicare-approved amount, and the supplier must be enrolled in Medicare. The details are in Medicare’s hospital bed policy and support surface policy and the state’s Medicaid DME manual (effective 1 July 2026).
| Item | Medicare Part B | New York Medicaid |
|---|---|---|
| Basic hospital bed | Covered if the person needs positioning not possible in an ordinary bed, needs it for pain, needs the head above 30 degrees most of the time (heart failure, chronic lung disease, aspiration), or needs traction. | Covered for a person who is bed-confined (not necessarily 100% of the time) and needs positioning not feasible in an ordinary bed. Rental is expected when the duration of need is unknown. |
| Height-adjustable or electric bed | Needs transfers or frequent position changes to qualify. Total electric is not covered. | Similar criteria. Semi-electric also requires that the person can use the controls. |
| Pressure-reducing mattress or overlay | A basic (Group 1) surface is covered for a person who is completely immobile, or has limited mobility or a pressure ulcer on the trunk or pelvis plus a risk factor such as impaired nutrition, incontinence, altered sensation or poor circulation. | Covered for a person who is bedridden or wheelchair-bound and/or has a documented history of pressure ulcers where regular cushioning failed. Air fluidized beds are not covered at home. |
A supplier or plan still has to approve the order, and rules change, so confirm with the doctor’s office and the supplier. Our guide to free medical equipment in New York covers other routes.
- Ask the doctor to write the order. Describe the real day, including pain, breathing trouble when flat and how often repositioning is needed.
- Use a supplier that takes the person’s insurance. For Medicare, ask if it is enrolled and accepts assignment. Medicaid bed codes need authorization, so ask the supplier to confirm it.
- Ask about renting and about training on the bed and mattress.
How often should a bedridden person be turned?
Sources differ, so the schedule should come from the person’s nurse or doctor. MedlinePlus lists changing position every two hours as a way to prevent pressure sores. The NIA late-stage caregiving page says at least every two hours in one list and at least every hour for someone lying down in another. A sample hospital plan in the AHRQ toolkit says every 1 to 2 hours for a bed-bound patient, with the head of the bed at 30 degrees or less unless breathing trouble or tube feeding requires more. It was written for hospitals, so treat it as a model, not home instructions.
AHRQ also notes that small shifts count: moving the person at least 15 to 20 degrees each time you enter the room. Other points from its materials:
- Avoid dragging the person across the sheet. For friction and shear risk, AHRQ’s plan uses at least two people and a draw sheet to pull someone up in bed.
- Do not massage bony areas and do not use donut-shaped ring cushions. AHRQ’s staff test marks both as false.
- Have a therapist or nurse teach you. Our in-home therapy page covers therapists who visit.
How do you check the skin and give a bed bath?
Look at the skin every day. NIA says to watch for discolored or darker spots on the heels, hips, lower back and back of the head, and to ask the doctor what to do if you find redness or sores. AHRQ adds that you should check skin under oxygen tubing, catheters or compression stockings, and each time you turn or clean the person. Our guides to bed sore prevention and pressure sore wound care go further.
For hygiene, NIA says a sponge bath of the face, hands, feet, underarms and private areas works on days a full bath is not possible, and that two or three baths a week is a reasonable target. Its bathing tips help with dignity: keep the room warm, tell the person each step before you do it, start with hands or feet, and cover the shoulders or lap with a towel. Hot water and soap can dry skin, per AHRQ’s staff test, so ask the nurse which products to use.
How do you prevent blood clots, pneumonia and stiff joints?
| Risk | What the sources say | When to get help |
|---|---|---|
| Blood clots (DVT, pulmonary embolism) | The CDC lists limited movement as a risk factor. About half of people with DVT have no symptoms. | Leg swelling, pain, warmth or redness: see a doctor soon. Trouble breathing, chest pain, coughing blood or fainting: seek medical help immediately. |
| Aspiration pneumonia | MedlinePlus lists swallowing problems and being fed when not upright as risk factors. | Chest pain, chills, fever, shortness of breath, bluish lips or tongue, wheezing: contact the provider, go to the emergency room or call 911. |
| Stiff joints (contractures) | NIA says a physical therapist can show you range-of-motion exercises. MedlinePlus says to follow the provider’s instructions on exercises, stretches, braces or splints. | Contact the provider if a contracture seems to be developing or a joint moves less than before. |
Do not start blood thinners, compression stockings or exercises on your own. Ask the prescriber or doctor. The CDC also lists signs of sepsis, including confusion, fever or shivering, a high heart rate and shortness of breath. Report them to a nurse or doctor right away.
How do you keep a bedridden person fed and safe from choking?
Swallowing gets harder in late illness, and NIA warns that food going into the lungs can cause pneumonia. NIA’s tips:

- Do not feed someone who is drowsy or lying down. They should sit upright for the meal and at least 20 minutes afterward.
- Offer small amounts, allow time to swallow, and use soft foods such as yogurt, applesauce or mashed sweet potatoes. Skip straws and use small sips from a cup.
- If the person is not getting enough calories, ask the doctor about supplements. If you suspect swallowing trouble, the doctor or home health team can test it. Our oral care guide covers mouth care.
How do you lift and move someone without hurting your back?
Lift less. The CDC’s NIOSH calls patient handling the single greatest injury risk factor for healthcare workers and recommends assistive lifting devices and training. OSHA lists repositioning in bed and lifting a patient in bed as potentially high-risk tasks.
- Get hands-on training from a nurse, aide or therapist first, and know your limits. NIA says to bend at the knees, keep your back straight and not bend at the waist.
- Ask the doctor or therapist whether a mechanical lift or transfer device suits this person, and have a trained person teach its use.
How many hands does it take, and when do you need an aide or a nurse?
There is no universal count. AHRQ’s sample hospital plan uses at least two people for pulling a bed-bound patient up, and the nurse or therapist who assesses the person should say which tasks need two. Ask about nights too: a person who needs turning overnight needs someone available overnight.
- An aide helps with bathing, toileting, feeding, turning and positioning, and transfers. See our personal care services page.
- A nurse assesses skin, sets the care plan and handles wounds, tubes and medication questions. See our nurse services page. Medicare’s home health benefit sends a nurse part-time, and Medicare.gov says an aide is covered only alongside skilled nursing or therapy. It does not cover 24-hour-a-day care or custodial care alone (see our Medicare home care guide).
- Respite keeps the family going. See our respite care guide.
What does New York Medicaid pay for when someone is bedridden?
For ongoing hours, most New York families look at Medicaid. The state’s CDPAP page and managed long term care page describe the options. People assessed on or after 1 September 2025 must meet a Minimum Needs Requirement: at least limited assistance with physical maneuvering with more than two activities of daily living, or supervision with more than one for someone with a dementia diagnosis. People already authorized or enrolled on that date continue under the older criteria.
| Option | How it works | Good to know |
|---|---|---|
| Personal care services (home attendant) | An agency aide, supervised by a nurse, under a plan of care. | Level II includes bathing in bed, toileting, transferring from bed to chair, and turning and positioning. See our Medicaid home care guide. |
| CDPAP | The person or a designated representative hires and directs the caregiver, who can be a relative with exceptions such as a spouse. | Requires a stable condition. See CDPAP eligibility. |
| Managed long-term care or PACE | A plan organizes home care, adult day health care and other services. | MLTCP and MAP need long-term care for more than 120 days. PACE is for age 55 and over with a nursing-home level of care. See PACE versus MLTC. |
New York’s personal care regulation, 18 NYCRR 505.14, defines two round-the-clock models. Continuous personal care is uninterrupted care by more than one aide for more than 16 hours a day, for a person whose need for help with toileting, walking, transferring, turning and positioning, or feeding is frequent enough that a live-in aide would be unlikely to get five hours of uninterrupted sleep. Live-in 24-hour care is one aide, where the need is infrequent enough that the aide likely would. An assessment decides which applies, if either. For private pay, see live-in care. To start with Medicaid, call the NYS Medicaid Helpline at 1-800-541-2831 (New York City: Human Resources Administration, 718-577-1399).
How many hours of Medicaid home care will be approved? Advice from our nurse director
Anna Klyauzova, RN, MSN, MPA, Director of Patient Services at ProLife Home Care, on what she sees in practice:
I never promise a family a number of hours before the assessment. Two people with the same diagnosis can need very different amounts of help. The assessment looks at how they manage daily activities, their cognitive state and other individual needs. If the approved hours still look too low, ask for a reassessment.
Don’t wait for a hospital stay or a fall to start looking at Medicaid and home care programs. It is far easier to arrange safe care before things reach a crisis.
ProLife Home Care is a licensed home care agency in Brooklyn and Queens, licence #2572L001, New York State Department of Health. We can talk through aide and nursing support and which parts Medicaid or Medicare may cover. Call (718) 232-2777 or use our contact page.
Coverage rules change. Everything above was checked on 12 October 2026 against medicare.gov, cms.gov, emedny.org, health.ny.gov, nia.nih.gov, ahrq.gov, medlineplus.gov, cdc.gov and osha.gov. Confirm your own situation with the person’s doctor, nurse, plan and supplier. This page is general information, not medical or legal advice.
Frequently asked questions
What does bedridden mean?
It describes a person who spends most or all of the day in bed because of illness, injury, frailty or weakness. New York Medicaid’s equipment rules say bed-confined does not have to mean 100% of the time. For care, what matters is how much the person can reposition without help.
Does Medicare pay for a hospital bed at home?
Medicare Part B may cover it when it is medically necessary and prescribed for use at home. You pay 20% of the approved amount after the deductible, and the supplier must be enrolled in Medicare.
Does New York Medicaid cover a hospital bed and pressure-relieving mattress?
Yes, if the written criteria are met. A hospital bed is covered for a bed-confined member whose condition needs positioning not possible in an ordinary bed, and a pressure-reducing surface for a bedridden or wheelchair-bound member, or one with a documented history of pressure ulcers.
How often should a bedridden person be turned?
Sources vary from every hour to every two hours, and the AHRQ hospital sample plan says every 1 to 2 hours. Ask the person’s nurse or doctor to set a schedule that fits their skin, mattress and condition.
Medicaid approved only 8 hours a day for a bedridden parent. What now?
Hours are set by an assessment, and no number is guaranteed. If they look too low for a person who needs turning, toileting and feeding, ask for a reassessment, describe the real day including nights, and ask whether the person’s needs fit the continuous or live-in 24-hour definitions.
Can one person safely care for a bedridden adult alone?
It depends on the person and the task. OSHA lists repositioning in bed and lifting a patient in bed as potentially high-risk tasks. Get hands-on training, ask the nurse which tasks need two people, and add an aide for those and for nights.
When should I call 911 for a bedridden person?
MedlinePlus and the CDC advise emergency help for chest pain, shortness of breath, bluish lips or tongue, or fainting, and the CDC lists confusion, fever and a fast heart rate among sepsis signs. For a new red or discolored area on the skin, call the nurse or doctor promptly.


